
关键词 人类免疫缺陷病毒(HIV);童年不良经历;相关性;范围综述
doi:10.12102/j.issn.1009-6493.2026.10.024
Adverse childhood experiences among people living with HIV: a scoping review GE Chunxing , QIAN Xiangyun , GAO Huiying , XIA Lanting , ZOU Meiyin
1. School of Nursing and Rehabilitation, Nantong University, Jiangsu 226000 China; 2. Nantong Third People's Hospital/Affiliated Nantong Hospital 3 of Nantong University
Corresponding Author QIAN Xiangyun, E-mail: qxy0306@163.com
Abstract Objective: To systematically examine the epidemiological characteristics of adverse childhood experiences(ACEs) among people living with human immunodeficiency virus(HIV) and to systematically examine the association between ACEs and health outcomes. Methods: This scoping review was guided by guidelines for scoping reviews from the Joanna Briggs Institute(JBI) Centre for Evidence-Based Healthcare of Australia. Eight databases(PubMed, Cochrane Library, CINAHL, EMbase, Web of Science, CNKI, Wanfang Database, and CBM) were systematically searched. Content extraction, synthesis, and analysis were performed on the included literature. Results: A total of 32 articles were included. The most frequently studied type of ACEs was sexual abuse, followed by physical abuse and emotional abuse. Data analysis revealed that from 82.5% to 95.0% of people living with HIV had experienced at least one ACE, and from 39.5% to 42.0% of people living with HIV had experienced≥4 ACEs. The impact of ACEs on the health outcomes and risk behaviors of people living with HIV encompassed physical, psychological, social functioning, substance use, and sexual risk behaviors. Conclusions: There is an association between ACEs and the health outcomes as well as high-risk behaviors among people living with HIV. However, current research on ACEs in this population remains insufficient, further in-depth investigation are needed in the future.
Keywords human immunodeficiency virus, HIV; adverse childhood experiences, ACEs; correlation; scoping review
童年不良经历(adverse childhood experiences, ACEs)指个体在0~17岁经历的各类创伤性事件,包含躯体/情感虐待、忽视、家庭功能障碍等核心维度[1]。累积暴露理论指出,ACEs与成年期身心健康损害存在剂量-反应关系[2-5]。已有研究显示,ACEs的累积暴露与抑郁、焦虑及物质使用障碍风险相关[6]; 80.9% 的中老年人经历过 ?1 种的ACEs,而暴露于 ?4 种ACEs者罹患心血管代谢疾病、呼吸系统疾病及神经精神共病的风险较未暴露者增加约2倍[2]。ACEs的高发率[7]及其对健康的长期影响已引起全球公共卫生领域的广泛关注。有学者发现,ACEs的暴露会增加成年后高风险性行为的发生[8],从而增加感染人类免疫缺陷病毒(HIV)的风险。一项针对美国HIV阳性
女性的Meta分析发现, 55%~72% 的受试者曾经历过童年或成年期的虐待,而ACEs的累积暴露与抗反转录病毒治疗(ART)依从性降低、病毒载量控制失败及共病风险增加相关[9]。目前,关于ACEs的流行病相关研究系统梳理较少,因此,本研究以澳大利亚乔安娜布里格斯研究所(JBI)循证卫生保健中心的范围综述指南[10]为指导,系统梳理HIV感染者ACEs暴露的流行病学特征及其与健康结局的关联,以期为改善遭受ACEs的HIV感染者的健康结局提供参考。
1 研究方法
1.1 确定研究问题
HIV感染者中ACEs的暴露率及类型分布(地域、性别)? ACEs对HIV感染者健康结局及风险行为有什么影响? 现有干预措施效果如何? 目前研究还存在哪些问题?
1.2 文献纳入与排除标准
纳入标准:1)年龄≥18岁,确诊为HIV阳性的病人;2)研究类型为定量、定性或混合方法研究;3)ACEs定义明确或有明确的测量工具。排除标准:1)重复发表,无法获取全文;2)信件、回复、会议摘要或方案类文章;3)语言非中文或英文;4)未区分童年与成年期创伤的研究;5)未报告ACEs暴露率、类型分布或与HIV结局关联的研究;6)研究对象为未确诊HIV的高危人群或未区分HIV感染状态。
1.3 文献检索
系统检索 PubMed、Cochrane Library、CINAHL、EMbase、Web of Science、中国知网、万方数据库和中国生物医学文献数据库8个数据库,并检索相关参考文献,检索时限为建库至2025年1月28日。采用自由词结合主题词的检索策略,中文主要检索词为HIV、艾滋病、人类免疫缺陷病毒、获得性免疫缺陷综合征、HIV感染者、AIDS患者、不良童年经历、童年逆境、童年创伤、儿童虐待、儿童忽视、躯体虐待、性虐待、情感虐待、家庭暴力、校园欺凌、父母酗酒、亲子分离、经济困难、父母吸毒、精神疾病、入狱;英文主要检索词为acquired immunodeficiency syndrome、HIV、AIDS、human immunodeficiency virus、people living with HIV、PLWHA、adverse childhood experiences、childhood adversity、child abuse、child neglect、child maltreatment、childhood trauma、domestic violence、parental substance abuse、parental mental disorder、parental incarceration、parental separation、household dysfunction、bullying、community violence、parental death、economic hardship、food insecurity。
1.4 文献筛选与资料提取
通过 EndNote 20.0 软件对检索到的文献去重,由两名经过系统培训的研究人员独立依据纳入与排除标准对文献标题和摘要进行初筛,再通过全文精读完成二次筛选。筛选过程中如遇分歧,与第3名研究者讨论解决,最终确定符合标准的文献。由两名研究者分别独立提取数据,包括作者及年份、国家、研究类型、样本量、ACEs 类型、ACEs 测量工具、主要结局指标、HIV 感染者中 ACEs 的暴露情况、中介变量、调节变量等。所有提取的数据均需经过交叉核对以确保准确性。
2 结果
2.1 文献筛选流程及结果
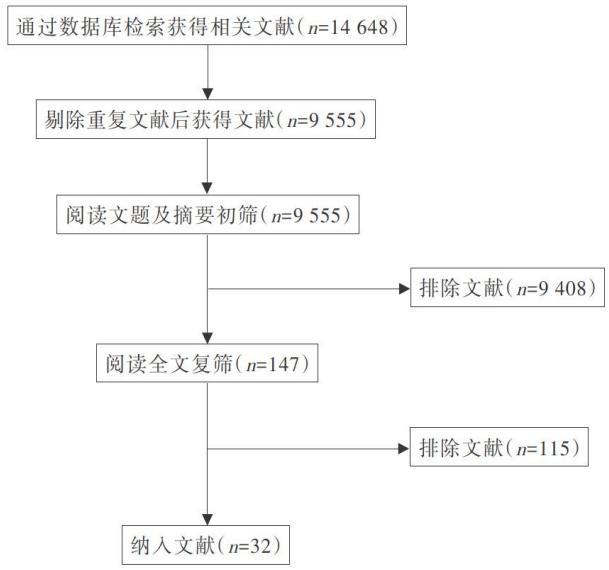
共检索到14648篇文献,剔除重复文献后剩余文献9555篇,阅读题目和摘要后排除文献9408篇,阅读全文后排除文献115篇,最终纳入文献32篇 [11-42] ,文献筛选流程及结果见图1。
图 1 文献筛选流程及结果
Figure 1 Literature screening process and results
2.2 纳入文献的基本特征
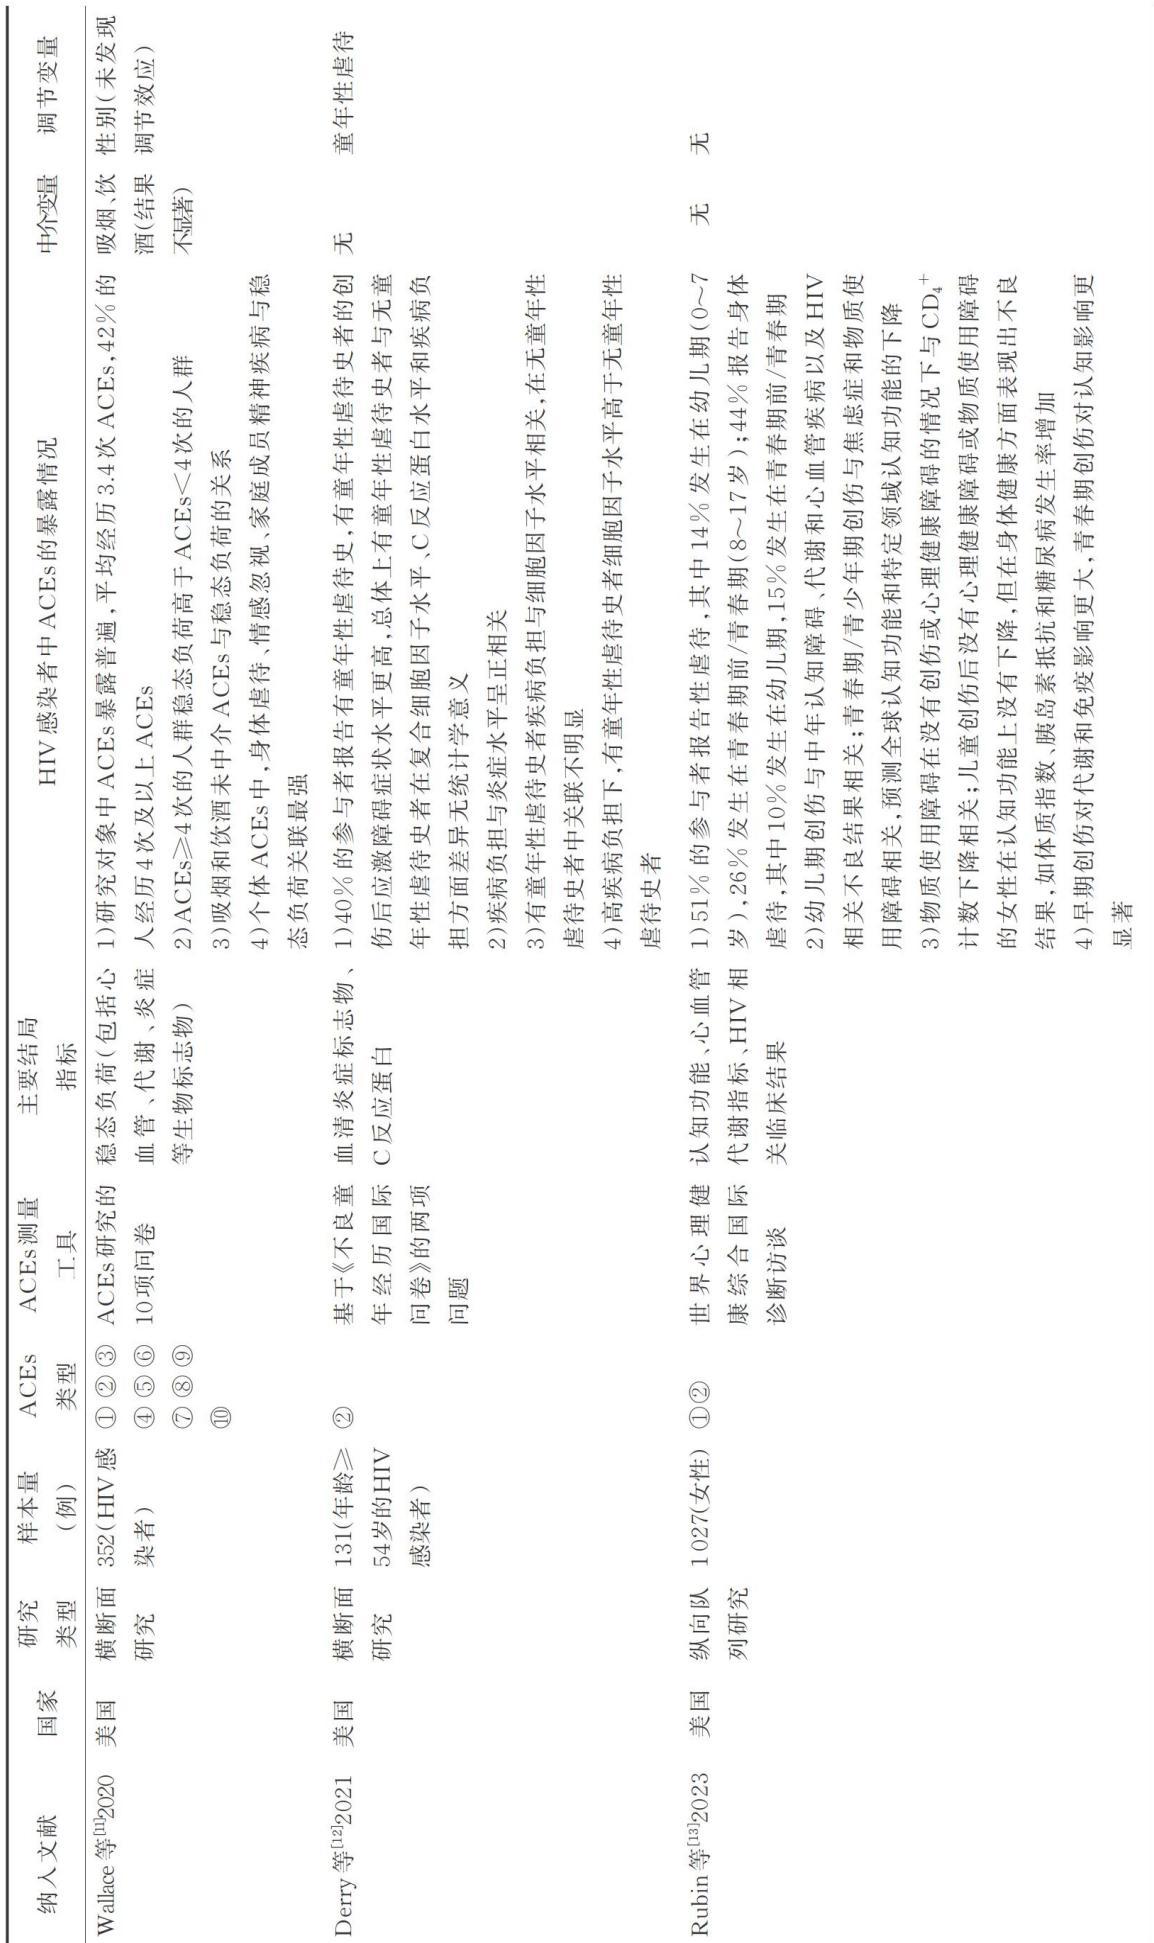
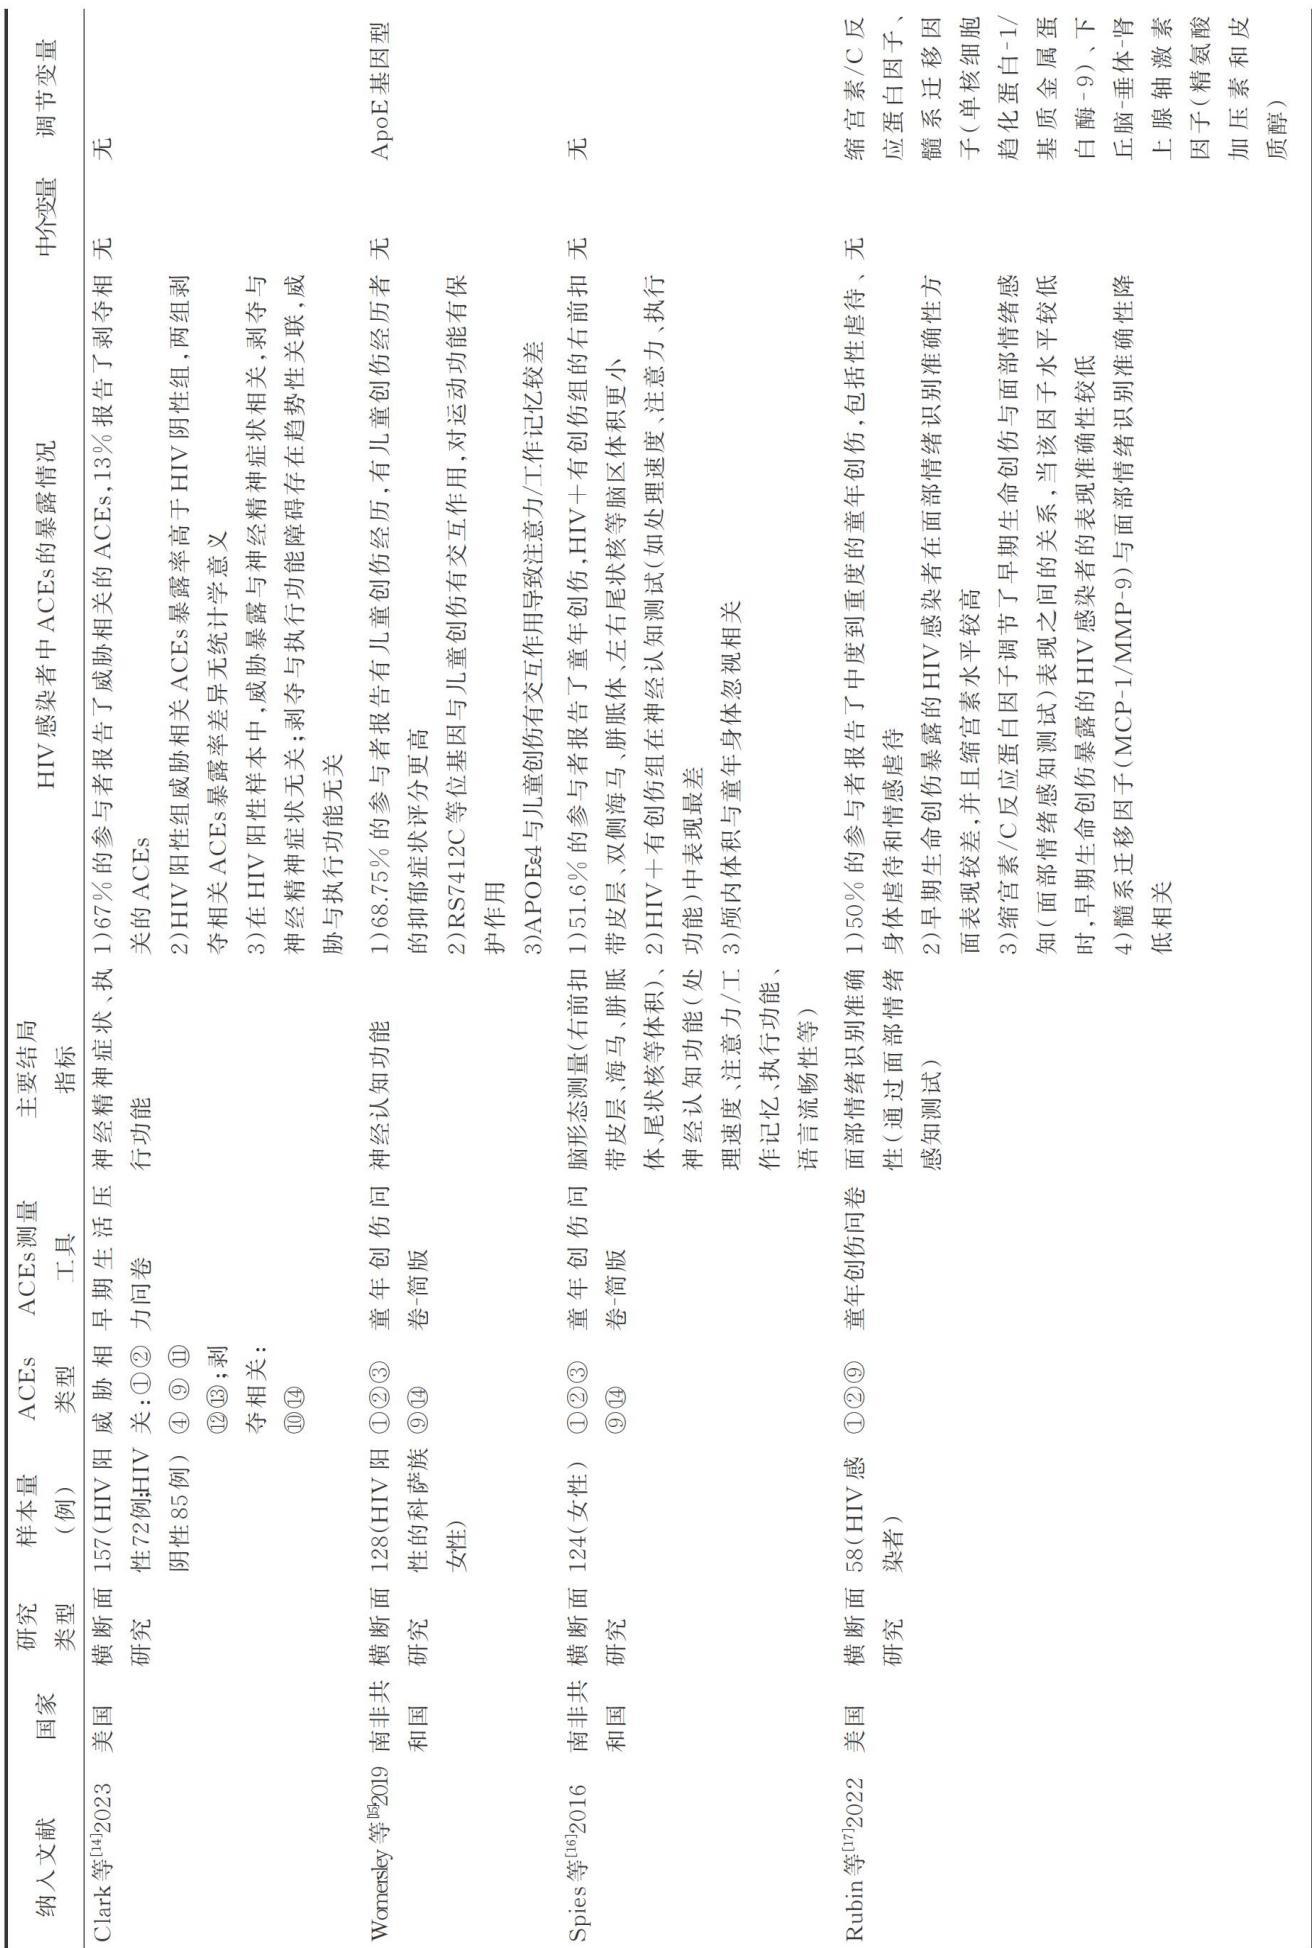
纳入的32篇文献中,美国进行的横断面研究[11-12,14,17-23,26-31,36-38,40]较多(20篇);研究对象包括男男性行为者、女性、中老年病人(≥50岁)、孕妇等;研究最多的ACEs类型是性虐待,其次是身体虐待、情感虐待。纳入文献的基本特征见表1。
表 1 纳入文献的基本特征
Table 1 Basic characteristics of the included studies
(续表)
(续表)

(续表)

注:①为身体虐待;②为性虐待;③为情感忽视;④为目睹过对母亲/照顾者的暴力行为;⑤为父母离婚或分居;⑥为家庭成员监禁;⑦为家庭成员物质滥用;⑧为家庭成员精神疾病或有自杀倾向;⑨为情感虐待;⑩为生活物资匮乏;?为欺凌;?为家庭冲突;?为战争;?为身体忽视;?为社区暴力;?为集体暴力;?为言语虐待;?为心理虐待;?为父母死亡;?为同伴暴力。
2.3 ACEs的暴露情况及其类型
本研究共纳入32项研究,样本量为24~1027例。在ACEs类型中,11项研究 [11,14-18,25,27,30,32-33] 评估了≥3种类型的ACEs,研究显示82.5%~95.0%的HIV感染者至少经历1次ACEs [25,27,32] ,39.5%~42.0%的个体经历≥4次ACEs [11,18] ;21项研究 [12-13,19-24,26,28-29,31,34-42] 评估的ACEs类型<3类,童年性虐待是其中的研究重点 [12-13,19-24,26,29,31,34-42] ,发生率为22.8% [19] ~56.0% [39] ,施暴者多为家庭成员或熟人 [41] 。性别方面,Villalba等 [39] 研究发现,63%的女性感染者报告曾遭受童年性虐待,而男性为49%;Markowitz等 [23] 研究显示,47.1%的参与者报告有童年性虐待经历,且男女之间差异无统计学意义。地域方面,部分非洲国家的研究 [25,32] 显示,社区暴力和家庭结构不稳定(如父母死亡、家庭暴力)影响ACEs发生,其中社区暴力的暴露率高达56% [32] ;而美国多数研究 [12,19-24,26,29,31,35-38,40-41] 则更关注童年性虐待对行为的影响。
2.4 ACEs 对 HIV 感染者健康结局及风险行为的影响
2.4.1 对健康结局的影响
2.4.1.1 生理
18项研究 [11-26,30,33] 调查了ACEs对HIV感染者生理健康的影响。结果显示,ACEs对生理健康产生了多方面的影响,主要体现在稳态负荷增加 [11] 、炎症水平升高 [12] 、神经认知功能受损 [16] 、催产素水平升高和面部情绪识别能力下降 [17] 等方面。然而,关于ACEs与HIV感染者免疫功能之间的关系,现有研究结果存在一定差异。部分研究表明ACEs通过间接途径损害免疫功能。Sauceda等 [19] 研究发现,童年性虐待通过加重抑郁症状影响ART的依从性,而低依从性直接影响免疫功能恢复进程。Markowitz等 [23] 研究发现童年性虐待与药物依从性差相关。Singh等 [25,33] 研究表明,病毒载量抑制与ACEs关联不明显。Sanders等 [18] 进一步指出,ACEs仅通过增加不健康天数间接影响生理健康,而与病毒抑制相关性不明显。
2.4.1.2 心理
14项研究 [12-13,19,25,27-28,30-33,35,37-38,41] 探讨了ACEs对HIV感染者心理健康的影响。结果表明,ACEs与多种心理障碍相关,包括抑郁、焦虑、创伤后应激障碍等。ACEs暴露可增加抑郁和焦虑症状风险 [19,25,28,32-33,37-38,41] 。Williams等 [35] 研究表明,干预后抑郁症状可明显减轻。Young-Wolff等 [27] 则发现,ACEs与焦虑和心理健康相关生活质量相关,但与抑郁、物质使用或HIV相关结局关联不明显。此外,具有童年性虐待史的个体通常表现出更高的创伤后应激障碍症状水平 [12] ,而童年创伤与童年性虐待、总体创伤后应激障碍症状、侵入症状、高警觉症状呈正相关 [31] 。
2.4.1.3 社会功能
社会支持与医疗资源利用及健康生活质量密切相关。Meade等 [26] 研究显示,社会支持不足可降低门诊治疗依从性,并与急诊服务使用增加相关。Persons等 [29] 研究发现,感知社会支持的可用性与较高的健康相关生活质量相关。此外,缺乏社会支持的个体更倾向于采用逃避或物质滥用作为应对策略 [34] ,导致性交和药物使用风险增加 [36] 。由于缺乏社会支持,部分病人甚至选择隐瞒或延迟披露HIV感染状态及遭受童年性虐待的经历 [41-42] 。
2.4.2 对风险行为的影响
2.4.2.1 物质使用
11项研究 [13,20,22-23,25,27-28,34,36,39-40] 讨论了ACEs与HIV感染者物质使用行为之间的关系,结果显示,其影响因年龄、性别及物质类别存在差异。从物质类别来看,Singh等 [25] 研究表明,经历 ?3 种ACEs的个体饮酒及烟草、大麻使用风险显著升高。Markowitz等 [23] 则指出在13~16岁经历童年性虐待的个体,在30 d内使用海洛因的风险更高。性别方面,Villalba等 [39] 发现,女性童年性虐待暴露者大麻使用风险尤为突出,男性关联不显著。在年龄方面,Brown等 [40] 的研究揭示,在老年HIV感染者中,童年性虐待史与阿片类药物使用风险存在关联,风险增加了21倍。然而,并非所有研究结论都一致。Young-Wolff等 [27] 研究未发现ACEs与物质使用之间的直接关联。
2.4.2.2 性行为风险
6项研究 [23-24,34,36,38-39] 表明童年性虐待会增加HIV感染者的性行为风险。Welles等 [38] 研究显示,有童年性虐待史的男性性接触次数及无保护肛交频率高于非暴露组。此外,童年性虐待作为核心风险因素,通过抑郁症状和情绪调节困难完全中介强迫性性行为的发生 [37] ,这一发现也在定量研究中得到了进一步验证 [24] 。
2.5 现有干预措施
纳入的32项研究中,仅Williams等 [35] 的研究进行了干预,结果显示,针对性健康干预可降低性风险行为及性伴侣数量,而标准健康促进干预效果有限;整体研究对象的抑郁症状在6个月随访时减少,组间差异无统计学意义。
3 讨论
3.1 ACEs暴露率及类型分布差异较大
本研究发现,ACEs暴露率因研究设计、样本特征及文化背景不同存在差异。部分研究显示,HIV感染者群体ACEs暴露率为82.5%~95.0% [27,32] ,这可能与HIV感染者的社会脆弱性密切相关,包括边缘化身份、经济困境及医疗资源获取障碍等。性别差异方面,Markowitz等 [23] 研究对象为有注射毒品史的HIV感染者,毒品使用可能掩盖性别特异性暴力差异,导致男女童年性虐待报告率差异不明显。南非共和国研究更强调社区暴力和家庭不稳定的高发性,这可能与社会动荡有关;而美国等国家则聚焦童年性虐待对个体行为的影响,反映文化对创伤敏感性的差异。这种差异提示未来ACEs的预防与干预需结合社会文化背景。
3.2 ACEs与健康结局和风险行为关系密切
ACEs与HIV感染者的心理健康、生理健康、社会功能和风险行为之间存在一定关联,但也应注意,ACEs类型、经历次数、个体年龄和性别等因素可能引起健康结局差异。此外,样本特征、研究方法和ACEs测量方式不同也可能导致结论差异。未来研究应更加深入地探讨ACEs的多维度影响,并考虑个体特征、文化背景和社会环境的作用,以更好地理解其对HIV感染者长期健康的影响。
3.3 研究局限性
3.3.1 干预措施匮乏
仅1项研究 [35] 评估了针对性健康干预的效果,且样本量有限。未来需结合文化背景、个体特征等开发针对HIV感染者的多层级干预方案。
3.3.2 ACEs测量工具不统一
纳入的32项研究中,部分研究使用标准化的ACEs问卷,如ACEs研究的10项问卷[11]、童年创伤问卷等[17,33,39];部分研究改编现有工具以适应特定群体或研究目的[12,18,22-23,26-27,34,36-37,42];还有部分研究采用自我报告或访谈形式[19,21,29,35,38,41],但尚未检索到研究在HIV人群中系统验证ACEs相关量表的重测信度或结构效度,导致跨群体比较可靠性存疑,未来需在HIV感染者中验证ACEs量表的信效度。此外,由于文化差异,不同研究对同类ACEs的操作定义存在分歧,未来应开发符合我国国情的ACEs特异性测量工具。
3.3.3 缺乏其他类型 ACEs 对 HIV 感染影响的研究
纳入的研究多聚焦于童年性虐待,这可能与童年性虐待对个体心理创伤严重有关,童年性虐待常引发羞耻感、信任问题 [41] 等心理困扰,这些负面情绪会直接或间接影响HIV感染者的行为,如高风险性行为或药物滥用,从而增加HIV传播风险或影响治疗依从性。此外,童年性虐待与HIV感染途径之间可能存在更直接的关联。经历童年性虐待的个体,成年后可能更容易从事无保护性行为 [36] ,或因心理创伤而滥用药物 [20] ,这些行为进一步增加了感染HIV的风险。未来研究应深入探讨其他类型ACEs对HIV感染者的独特影响以及不同类型ACEs对HIV感染者的综合影响,并探索地区间的差异,以便制定更加精准的干预策略。
3.3.4 机制探索不足
尽管部分研究揭示了抑郁症状、情绪调节困难等中介路径,但多数机制研究仍停留在相关性分析层面。未来需整合神经影像学、表观遗传学等多种学科,探索ACEs通过表观修饰、下丘脑-垂体-肾上腺轴失调等生物学途径影响HIV感染者的健康机制。
4 小结
本研究对HIV感染者中ACEs的研究情况进行范围综述,系统梳理了HIV感染者中ACEs的暴露率、类型及其对健康结果和风险行为的影响。结果表明,ACEs在HIV感染者中的发生率受研究设计、样本特征和文化背景的影响。尽管不同研究在ACEs与HIV感染者健康结局及高风险行为之间的结论存在差异,但两者之间存在密切关联。目前关于ACEs与HIV感染者的研究还存在不足,且我国相关研究较少,未来需结合个体特征、文化背景等进行深入研究,并设计合适的干预方案预防和减少HIV感染者的ACEs暴露问题,改善遭受ACEs的HIV感染者健康结局。
参考文献:
[1] World Health Organization. Adverse Childhood Experiences International Questionnaire(ACE-IQ)[EB/OL].[2025-03-07].https://www.who.int/publications/m/item/adverse-childhood-experiences-international-questionnaire-(ace-iq).
[2] LIN L, WANG H H, LU C Y, et al. Adverse childhood experiences and subsequent chronic diseases among middle-aged or older adults in China and associations with demographic and socioeconomic characteristics[J]. JAMA Network Open, 2021, 4(10): e2130143.
[3] ZHANG T T, KAN L N, JIN C B, et al. Adverse childhood experiences and their impacts on subsequent depression and cognitive impairment in Chinese adults: a nationwide multi-center study[J]. J Affect Disord, 2023, 323:884-892.
[4] BR?NN E, VAINA A, DAN?ELSD?TTIR H B, et al. Association between adverse childhood experiences and perinatal depressive symptoms: a cross-sectional analysis of 16 831 women in Iceland[J]. Arch Womens Ment Health, 2023, 26(6):839-849.
[5] MUWANGUZI M, KAGGWA M M, NAJJUKA S M, et al. Exploring adverse childhood experiences(ACEs) among Ugandan University students:its associations with academic performance, depression, and suicidal ideations[J].BMC Psychology, 2023, 11(1):11.
[6] DAN?ELSD?TTIR H B, ASPELUND T, SHEN Q, et al. Adverse childhood experiences and adult mental health outcomes[J]. JAMA Psychiatry, 2024, 81(6):586-594.
[7] MADIGAN S, THIEMANN R, DENEAULT A A, et al. Prevalence
of adverse childhood experiences in child population samples: a systematic review and meta-analysis[J].JAMA Pediatrics, 2025, 179(1):19–33.
[8] BERTOLINO D F, SANCHEZ T H, ZLOTORZYNSKA M, et al. Adverse childhood experiences and sexual health outcomes and risk behaviors among a nationwide sample of men who have sex with men[J]. Child Abuse Negl, 2020, 107:104627.
[9] MACHTINGER E L, WILSON T C, HABERER J E, et al. Psychological trauma and PTSD in HIV-positive women: a meta-analysis[J]. AIDS and Behavior, 2012, 16(8):2091-2100.
[10] PETERS M D J, MARNIE C, TRICCO A C, et al. Updated methodological guidance for the conduct of scoping reviews[J]. JBI Evid Implement, 2021, 19(1):3-10.
[11] WALLACE M, FELKER-KANTOR E, MADKOUR A, et al. Adverse childhood experiences, smoking and alcohol use, and allostatic load among people living with HIV[J]. AIDS Behav, 2020, 24(6): 1653-1662.
[12] DERRY H M, JOHNSTON C D, BRENNAN-ING M, et al. Childhood sexual abuse history amplifies the link between disease burden and inflammation among older adults with HIV[J]. Brain, Behavior & Immunity-Health, 2021, 17:100342.
[13] RUBIN L H, MAKI P M, DASTGHEYB R M, et al. Trauma across the life span and multisystem morbidity in women with HIV [J]. Psychosom Med, 2023, 85(4):341-350.
[14] CLARK U S, HERRINGTON O D, HEGDE R R. Effects of early–life adversities on neuropsychiatric and executive functions in HIV–positive adults[J]. J Int Neuropsychol Soc, 2023, 29(1):68–79.
[15] WOMERSLEY J S, SPIES G, SEEDAT S, et al. Childhood trauma interacts with ApoE to influence neurocognitive function in women living with HIV[J]. J Neurovirol, 2019, 25(2):183-193.
[16] SPIES G, AHMED-LEITAO F, FENNEMA-NOTESTINE C, et al. Effects of HIV and childhood trauma on brain morphometry and neurocognitive function[J]. Journal of Neuro Virology, 2016, 22(2):149-158.
[17] RUBIN L H, BHATTACHARYA D, FUCHS J, et al. Early life trauma and social processing in HIV: the role of neuroendocrine factors and inflammation[J]. Psychosom Med, 2022, 84(8):874-884.
[18] SANDERS R, DOMBROWSKI J C, HAJAT A, et al. Associations between adverse childhood experiences, viral suppression, and quality of life among persons living with HIV in Washington state [J]. AIDS Care, 2024, 36(7): 937–945.
[19] SAUCEDA J A, WIEBE J S, SIMONI J M. Childhood sexual abuse and depression in Latino men who have sex with men: does resilience protect against nonadherence to antiretroviral therapy? [J]. J Health Psychol, 2016, 21(6):1096-1106.
[20] BROWN M J, ZHANG J, ADDO P N O, et al. Childhood sexual trauma, substance use, and antiretroviral therapy adherence among older adults living with HIV: a mediational analysis[J]. J Appl Gerontol, 2025, 44(2):222-230.
[21] WILSON S M, SIKKEMA K J, RANBY K W. Gender moderates the influence of psychosocial factors and drug use on HAART adherence in the context of HIV and childhood sexual abuse[J]. AIDS Care, 2014, 26(8): 959–967.
[22] LIU H H, LONGSHORE D, WILLIAMS J K, et al. Substance abuse and medication adherence among HIV-positive women with histories of child sexual abuse[J]. AIDS Behav, 2006, 10(3):279-286.
[23] MARKOWITZ S M, O'CLEIRIGH C, HENDRIKSEN E S, et al. Childhood sexual abuse and health risk behaviors in patients with HIV and a history of injection drug use[J]. AIDS Behav, 2011, 15(7):1554-1560.
[24] BROWN M J, JAMES T, KAUR A, et al. Childhood sexual abuse and antiretroviral therapy adherence among older adults living with HIV: a mixed methods study[J]. AIDS Care, 2024, 36(1):17-25.
[25] SINGH N P, NTLANTSANA V, TOMITA A, et al. Childhood trauma, substance use and depressive symptoms in people with HIV during COVID-19[J]. The South African Journal of Psychiatry,
2024,30:2220.
[26] MEADE C S, HANSEN N B, KOCHMAN A, et al. Utilization of medical treatments and adherence to antiretroviral therapy among HIV-positive adults with histories of childhood sexual abuse[J]. AIDS Patient Care and STDs, 2009, 23(4):259-266.
[27] YOUNG-WOLFF K C, SAROVAR V, STERLING S A, et al. Adverse childhood experiences, mental health, substance use, and HIV-related outcomes among persons with HIV[J]. AIDS Care, 2019, 31(10):1241-1249.
[28] KAMEN C, BERGSTROM J, VORASARUN C, et al. The impact of childhood bullying among HIV-positive men: psychosocial correlates and risk factors[J]. Child Abuse Negl, 2013, 37(4):273-281.
[29] PERSONS E, KERSHAW T, SIKKEMA K J, et al. The impact of shame on health-related quality of life among HIV-positive adults with a history of childhood sexual abuse[J]. AIDS Patient Care and STDs, 2010, 24(9):571-580.
[30] GASIK R E, MADKOUR A S, SKEEN S J, et al. The impact of childhood adversity on life course alcohol use patterns and health status among people living with HIV[J]. AIDS Behav, 2024, 28(9): 2887-2898.
[31] KAMEN C, BERGSTROM J, KOOPMAN C, et al. Relationships among childhood trauma, posttraumatic stress disorder, and dissociation in men living with HIV/AIDS[J]. Journal of Trauma & Dissociation, 2012, 13(1):102–114.
[32] MASIANO S P, YU X Y, TEMBO T, et al. The relationship between adverse childhood experiences and common mental disorders among pregnant women living with HIV in Malawi[J]. J Affect Disord, 2022, 312:159–168.
[33] WALTON G, CO S J, MILLOY M J, et al. High prevalence of childhood emotional, physical and sexual trauma among a Canadian cohort of HIV-seropositive illicit drug users[J]. AIDS Care, 2011, 23(6):714-721.
[34] CLUM G A, ANDRINOPOULOS K, MUESSIG K, et al. Child abuse in young, HIV-positive women: linkages to risk[J]. Qualitative Health Research, 2009, 19(12):1755-1768.
[35] WILLIAMS J K, WYATT G E, RIVKIN I, et al. Risk reduction for HIV-positive African American and Latino men with histories of childhood sexual abuse[J]. Arch Sex Behav, 2008, 37(5):763-772.
[36] SIKKEMA K J, HANSEN N B, MEADE C S, et al. Psychosocial predictors of sexual HIV transmission risk behavior among HIV-positive adults with a sexual abuse history in childhood[J]. Arch Sex Behav, 2009, 38(1):121-134.
[37] BROWN M J, OSINUBI M O, AMOATIKA D, et al. Childhood sexual abuse and compulsive sexual behavior among men who have sex with men newly diagnosed with HIV[J]. AIDS and Behav, 2024, 28(10):3421-3429.
[38] WELLES S L, BAKER A C, MINER M H, et al. History of childhood sexual abuse and unsafe anal intercourse in a 6-city study of HIV-positive men who have sex with men[J]. Am J Public Health, 2009, 99(6):1079-1086.
[39] VILLALBA K, ATTONITO J, JEAN-GILLES M, et al. Gender differences in the association between childhood sexual abuse and risk behaviors among people living with HIV in Haiti[J]. AIDS Care, 2020, 32(11):1438-1444.
[40] BROWN M J, SUNKARA S, KAUR A, et al. Childhood sexual trauma and opioid use among older adults living with HIV[J]. AIDS Care, 2024, 36(12):1852-1857.
[41] KAUR A, BROWN M J, JAMES T A, et al. Stories of childhood sexual abuse(CSA) among older adults living with HIV(OALH) in South Carolina:a qualitative study[J].AIDS Care, 2024, 36(2):272-279.
[42] CLUM G A, CZAPLICKI L, ANDRINOPOULOS K, et al. Strategies and outcomes of HIV status disclosure in HIV-positive young women with abuse histories[J]. AIDS Patient Care STDS, 2013, 27(3):191-200.
(收稿日期:2025-05-27;修回日期:2026-02-09)
(本文编辑 陈琼)



